Gallbladder removal (cholecystectomy) is one of the most common elective surgeries performed worldwide, and a meaningful share of patients continue to have digestive symptoms afterward — loose stools, bile acid diarrhea, and discomfort after fatty meals. Because TUDCA (tauroursodeoxycholic acid) is a bile acid itself, people researching gallbladder health and post-surgical recovery frequently ask whether supplementing with it makes physiological sense.
This article looks at what bile flow research actually shows about the gallbladder, bile duct physiology after cholecystectomy, and where TUDCA-specific data exists versus where the connection is inferred from broader bile acid science.
Key Takeaways
- After cholecystectomy, bile flow is no longer stored and concentrated by the gallbladder — it drips continuously from the liver into the duodenum, governed mainly by intraductal pressure and sphincter activity.[1]
- Human research directly comparing TUDCA and UDCA found both bile acids affect gallbladder emptying and contractility in gallstone patients, though the two are not identical in effect.[2]
- In a mouse model of a lithogenic (stone-forming) diet, TUDCA supplementation prevented full cholesterol gallstone formation seen in the untreated group, tied to changes in intestinal lipid absorption and gut microbiota.[3]
- Most of the clinical-trial-grade human evidence for TUDCA outside the gallbladder is in liver and metabolic contexts, not gallbladder-specific outcomes — the gallbladder literature is smaller and older.
- Anyone with an intact gallbladder, active gallstones, or a recent cholecystectomy should discuss any bile acid supplement with their surgeon or gastroenterologist before use, since bile acid supplementation history is mixed and condition-dependent.
How Bile Flow Changes After Gallbladder Removal
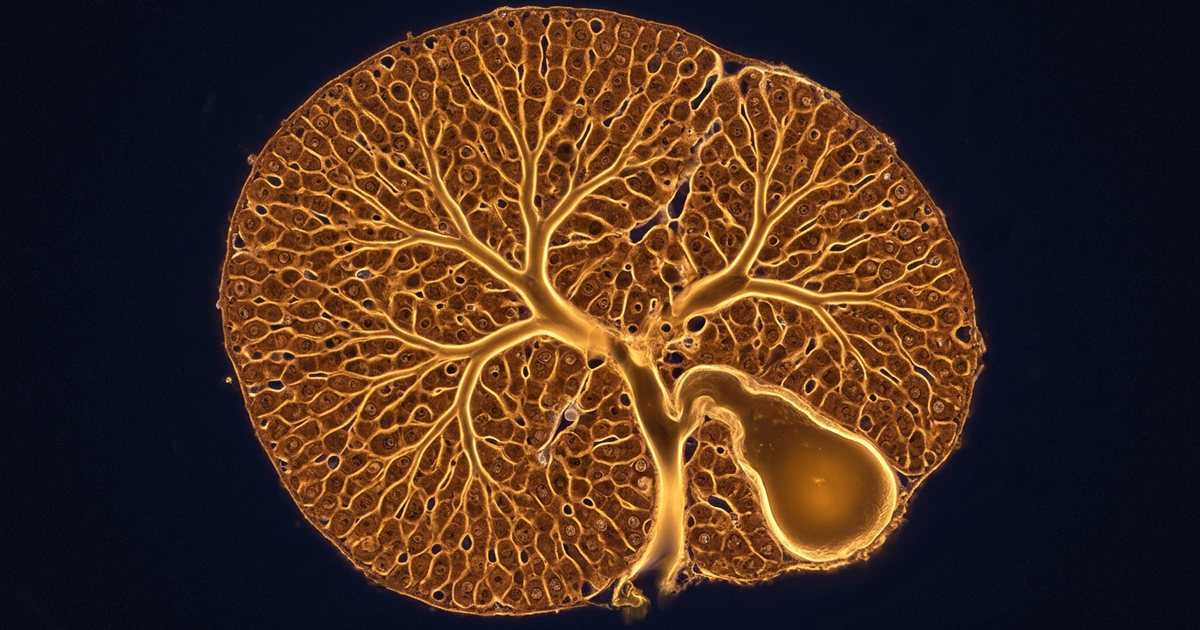
The gallbladder’s normal job is to store and concentrate bile between meals, then contract and release a concentrated bolus when fat enters the duodenum. Once it is removed, that reservoir function is gone. Bile now flows in a more continuous, lower-concentration stream directly from the liver through the common bile duct.
Older but still-cited physiology research using T-tube drainage in post-cholecystectomy patients found that the bile duct itself has no significant intrinsic motility of its own. Instead, flow is governed by the pressure the liver generates, the resistance of the duct and the sphincter of Oddi at its terminal end, and pressure inside the duodenum. Researchers observed rhythmic arrests in flow attributed to sphincteric contraction, meaning the sphincter — not the missing gallbladder — becomes the main regulator of how and when bile reaches the gut.[1] This is the physiological backdrop for why some post-cholecystectomy patients experience unpredictable bile delivery: too much bile hitting the gut at once can contribute to bile acid diarrhea, while poor timing relative to meals can affect fat digestion.
What TUDCA-Specific Research Shows
Most TUDCA research relevant to the gallbladder falls into two categories: motility studies in people who still have gallstones, and prevention studies in animal models of gallstone formation.

A human study comparing TUDCA and UDCA administration in both gallstone patients and healthy subjects measured gallbladder emptying and contractile response. Both bile acids influenced gallbladder motility, supporting the general idea that hydrophilic bile acids like TUDCA are not inert with respect to gallbladder function — though the study’s scope was motility, not stone dissolution or long-term outcomes.[2]

In an animal model, mice fed a lithogenic (gallstone-promoting) diet developed cholesterol gallstones with cholesterol crystals in 100% of untreated animals. Mice fed the same diet plus TUDCA showed cholesterol crystals in only a small number of animals, and no mouse in the TUDCA group developed a full gallstone. The researchers linked this protective effect to TUDCA’s influence on intestinal lipid absorption and gut microbiota composition, not simply to bile acid replacement.[3] Animal-model results like this are useful for generating hypotheses about mechanism, but they do not establish that oral TUDCA supplementation prevents gallstones in humans — that trial has not been done.
Bile Acid Diarrhea and Post-Surgical Digestive Symptoms
A notable share of post-cholecystectomy patients develop bile acid diarrhea, thought to result from bile acids reaching the colon in higher concentration or more erratically than before surgery, where they stimulate colonic secretion and motility. This is a distinct problem from gallstone formation, and it is not obvious that adding another bile acid — even a relatively gentle, hydrophilic one like TUDCA — is the right intervention for someone already dealing with excess bile acid delivery to the colon. This is precisely the kind of individual variation where self-directed supplementation without medical guidance carries real risk of making symptoms worse rather than better.
Where the Evidence Is Thin
It’s worth being direct about the limits here. There is no large randomized controlled trial testing oral TUDCA supplementation specifically in post-cholecystectomy patients for symptom relief or bile-flow normalization. The motility study above included gallstone patients, not post-surgical patients. The gallstone-prevention data is a mouse model, not a human trial. People considering TUDCA in this context should understand they are extrapolating from adjacent research, not following a body of direct, condition-specific clinical evidence.
Practical Considerations
For someone with an intact gallbladder and gallstones, TUDCA has not been studied as a stone-dissolution agent the way UDCA has (UDCA holds regulatory approval for cholesterol gallstone dissolution in some countries). For someone post-cholecystectomy dealing with bile acid diarrhea, adding a bile acid supplement without medical supervision is not obviously the right move and could plausibly worsen symptoms. For someone using TUDCA for unrelated reasons (liver support, ER stress research interest) who happens to have gallbladder history, that history is a specific reason to loop in a physician rather than assume general TUDCA safety data applies unchanged.

As with any bile-acid-related supplement decision involving a surgical history or active gallbladder disease, this is a conversation for a surgeon or gastroenterologist, not a decision to make from general research alone.
Frequently Asked Questions
Does TUDCA dissolve gallstones like UDCA?
TUDCA has not been studied as a gallstone-dissolution therapy in humans the way UDCA has. UDCA holds regulatory approval in some countries for dissolving small cholesterol gallstones; TUDCA’s gallbladder research is limited to motility studies and one animal prevention model, not human dissolution trials.
Can I take TUDCA after gallbladder removal?
There is no dedicated clinical trial testing TUDCA in post-cholecystectomy patients. Because many people develop bile acid diarrhea after this surgery, adding a bile acid supplement without medical guidance could plausibly worsen rather than improve symptoms. Talk to your surgeon or gastroenterologist first.
What causes digestive symptoms after gallbladder removal?
Without a gallbladder to store and concentrate bile, bile flows more continuously and less predictably into the duodenum, governed largely by intraductal pressure and the sphincter of Oddi. This can lead to bile acid diarrhea when bile acids reach the colon in higher concentrations than before surgery.
Is there human evidence that TUDCA prevents gallstones?
The clearest prevention evidence is a mouse study, where TUDCA supplementation prevented full gallstone formation in animals fed a stone-promoting diet, linked to effects on intestinal lipid absorption and gut microbiota. This has not been replicated in a human clinical trial.
References
- Flow through the bile duct after cholecystectomy. Gut (1975). PMID 1129682
- Tauroursodeoxycholic acid, ursodeoxycholic acid and gallbladder motility in gallstone patients and healthy subjects. Journal of hepatology (1996). PMID 8782006
- The effect of Tauroursodeoxycholic acid (TUDCA) and gut microbiota on murine gallbladder stone formation. Annals of hepatology (2021). PMID 33217585
These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure, or prevent any disease. Content is for informational purposes only and is not medical advice; consult a qualified healthcare provider before starting any supplement. As an Amazon Associate we earn from qualifying purchases.
